Pain is not a luxury problem in emergency treatment, it is the here and now sign that shapes every choice you make in the very first minutes. Treat pain properly and you obtain trust fund, improve assessment accuracy, and usually prevent issues. Get it wrong and the entire experience turns. The approved device PUAEME008 Supply pain monitoring sits directly in that room. It gives paramedics, initially responders, event paramedics, and medical support staff a practical, defensible structure to decrease discomfort safely in unrestrained environments.
I have actually shown and executed this unit throughout ambulance solutions and remote centers, and the same styles repeat: the protocols look easy on paper, yet real scenes are messy. You need to protect a view to what matters most, scoot without cutting edges, and record as if an auditor rides in the dive seat. This article breaks down what the training covers, why it is structured the way it is, and just how it links to broader discomfort management training courses for nurses and physiotherapists that support prehospital groups or run in urgent-care settings.
Where PUAEME008 Suits the Training Landscape
The PUAEME008 provide pain management system is normally nested within public security and emergency response qualifications. You will see it coupled with basic life support, oxygen therapy, and analgesia modules in certificate-level bundles designed for functional responders. It does not pretend to be a thorough discomfort fellowship, and that is appropriate. The focus is secure, timely analgesia with restricted sources, usually prior to a clear-cut medical diagnosis exists.
For medical professionals coming from medical facilities, this can seem like a step down in pharmacology depth, however actually it is an action up in risk monitoring. Emergency discomfort administration on an aesthetic at 3 a.m. varies from an ED work area with full monitoring and drug store access. The device adjusts decisions to that area reality: quick assessments, repeat monitorings, conservative dosing, and solid focus to contraindications that are easy to miss when the wind is up and the patient is light and sweating.
This system can sit alongside a certificate program in pain administration provided to multidisciplinary staff. The distinction is focus. A discomfort administration certification course in a medical facility system studies multimodal and chronic frameworks. PUAEME008 anchors intense, typically distressing, presentations with short half-life options, simple delivery systems, and unambiguous documentation.
What the Device Actually Covers
Training suppliers differ in delivery, yet the core results remain steady. You learn to analyze discomfort quickly using typical scales, to pick appropriate analgesic paths within your range, to provide, check, and afterwards reassess. You likewise find out to rise when the picture does not fit or pain continues to be uncontrolled.
Typical scope consists of:
- Scene-based evaluation and differential framework of pain in the very first 5 minutes: injury versus medical, warnings that suggest time-critical pathology, and just how pain itself can mask or mimic severity. Analgesic alternatives aligned with the responder's scope and jurisdiction. The acquainted trio is breathed in methoxyflurane where allowed, oral or transmucosal agents, and simple parenteral options for those recommended. Some solutions include intranasal opioids or ketamine under details procedures. The device shows indication thresholds and stop rules. Non-pharmacological techniques like placing, immobilisation, splinting, ice or heat when appropriate, diversion, and guided breathing. In busy changes these obtain ignored, yet they typically reduced discomfort scores by two or 3 factors prior to any medicine takes effect. Monitoring for efficiency and damaging results. You find out to cycle observations at defined periods and to correlate subjective discomfort ratings with unbiased markers: respiratory price, end-tidal carbon dioxide where available, mental condition, perfusion, and movement. Communication and authorization. The device stresses explaining alternatives simply, acquiring educated consent or continuing under indicated approval where capability is impaired, and recording the rationale in clear language.
The assessment is functional. You run through circumstances that vary from an ankle fracture at a sports occasion to a baffled older grown-up with stomach discomfort. Trainers will certainly view how you verbalise threat, exactly how promptly you discover altering vitals, and whether you ask for aid early. Paper understanding assists, however it is the routines under time stress that pass or stop working you.
Why Emergency Discomfort Monitoring Demands a Various Lens
In controlled environments it is very easy to construct a perfect pain ladder. Out in the open, concerns change. One of the most common mistake I see is false precision, a tendency to look for the ideal medical diagnosis prior to delivering first-line alleviation. In a roadside crash with an obvious deformity, awaiting a full differential misreads. Pain itself drives tachycardia and hyperventilation, gets worse anxiousness, and blocks significant evaluation. Analgesia becomes an analysis tool. As the discomfort drops, you can palpate, reposition, and test work more accurately.
The 2nd difference is authorization under uncertainty. The patient is frequently nervous, hypoxic, or intoxicated. You still aim for permission, however you frame it crisply. "I can supply a fast-acting breathed in discomfort medicine. It disappears rapidly, some individuals really feel lightheaded. Would certainly you such as that while we splint your leg?" After that you pause, watch their eyes, pay attention for the yes. Good training teaches this cadence.

Finally, the device respects that -responders often function alone or as a pair without a doctor on the radio. Procedures should be clear, not depending on lengthy consults. If the policy allows methoxyflurane up to a specified maximum, you discover to dosage, display, and quit within those borders. If intranasal fentanyl is included, you discover exact volumes per nostril, spacing, and saturation limits that cause a change of plan.
The Pharmacology You Actually Use
Most PUAEME008-aligned programs prioritise agents that are portable, fast-onset, and very easy to titrate. Precise formularies depend on the service, yet several patterns appear again and again.
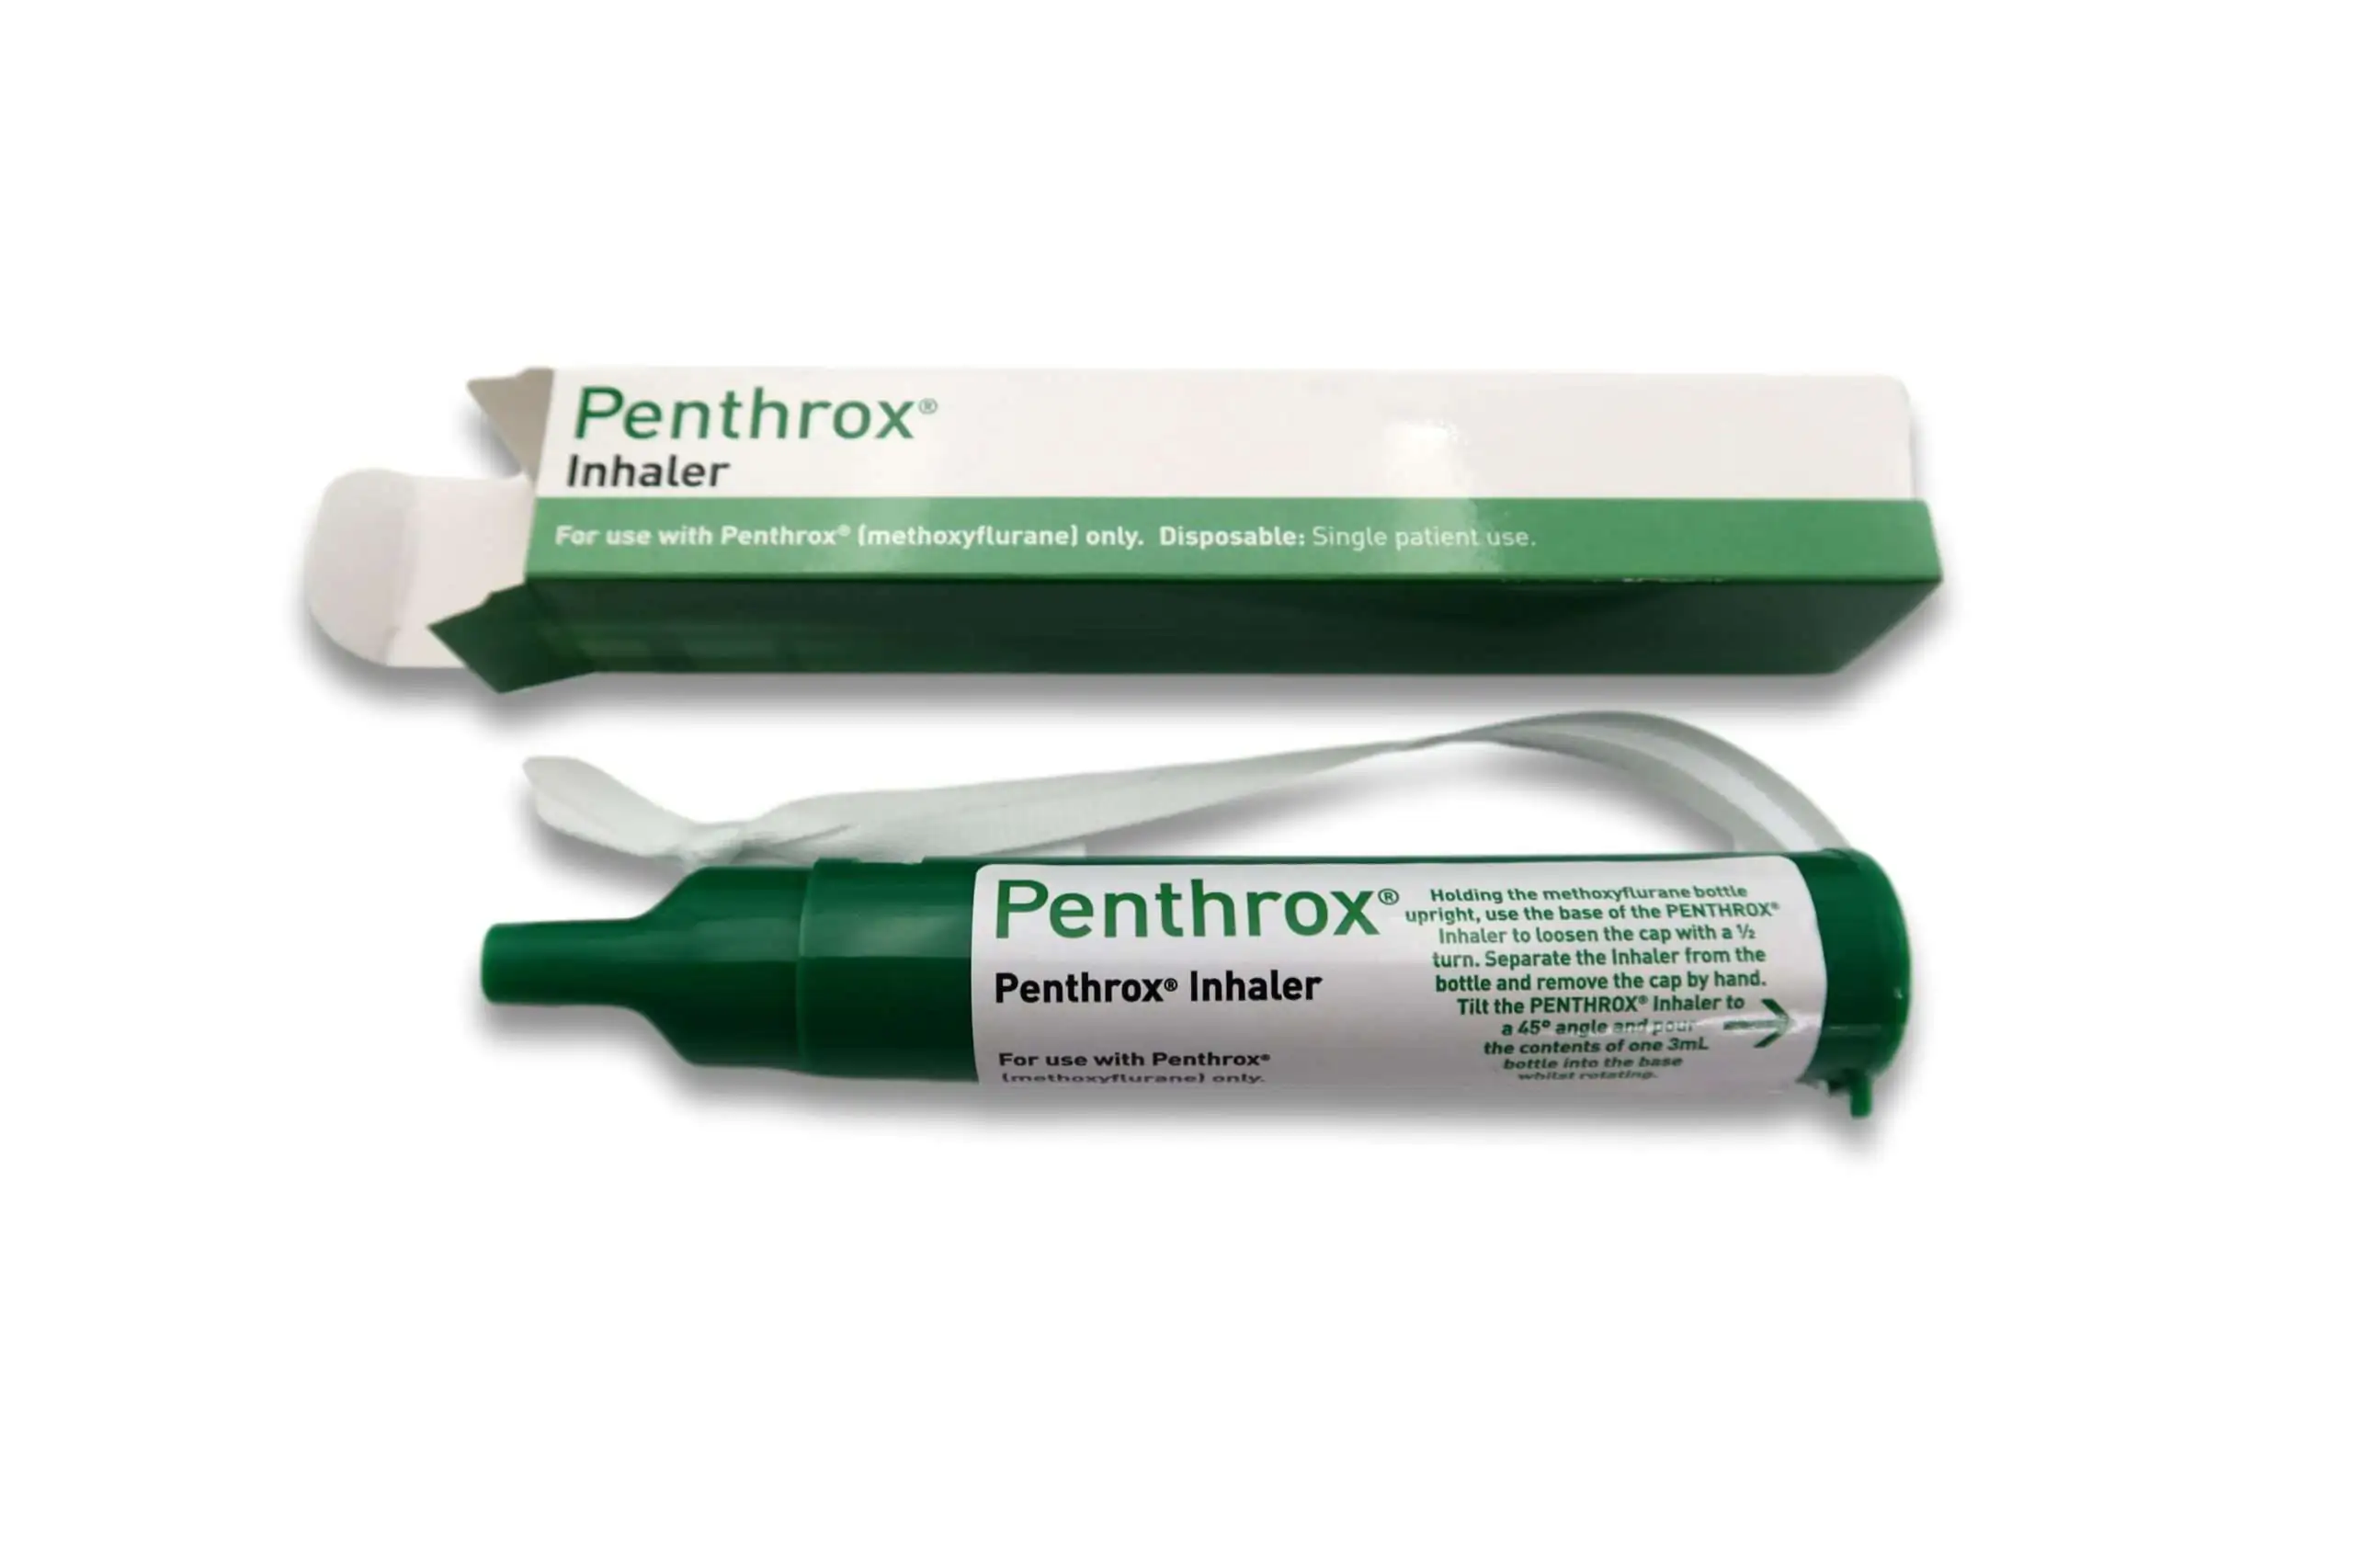
Methoxyflurane, where readily available, is an area workhorse. It is inhaled, self-administered with mentoring, and it permits a secured kind of self-titration. The training stresses guidance, restricting total dose, and recognising when a patient's strategy falls short as a result of frustration or fatigue. It also shows environmental safety and security. The smell is unique, and in improperly aerated spaces suppliers can feel dull or headachy. Crack a window, action outside if useful, and rotate tasks so the exact same team member does not hover by the mouth piece for twenty minutes.
Intranasal opioids, typically fentanyl, load the space when inhaled options are contraindicated or poor. The intranasal course avoids needle stick threat and relocates promptly via vascular nasal tissue. You find out to split the dose in between nostrils, readjust for age and frailty, and pay ruthless focus to respiratory tract tone once discomfort declines. You practice what to do if respiratory system rate slips below thresholds, when to rearrange, when to add oxygen, and when to reverse.
Ketamine, in some extended-scope services, gains its area for distressing discomfort that withstands other agents, particularly when hypotension makes opioids high-risk. The unit does not transform responders into anaesthetists. It insists on precise dosing, clear contraindications like psychosis, and robust surveillance. The advantage is tremendous in remote setups where extrication and stretcher movement turn mins into an hour.
Paracetamol and non-steroidal anti-inflammatories do not grab headlines, but their additive impact issues. Early enteral dosing alongside fast-acting representatives develops a bridge that holds via transport and handover. The system instructs secure NSAID use, renal cautions, and gastric defense for older adults.
Non-Drug Strategies That Issue Greater Than You Think
Every discomfort management program speaks up non-pharmacological approaches. In emergency care, those methods are not "great to have." They are the initial treatment. Splinting an unsteady ankle joint, extra padding a backboard pressure point, elevating an arm or leg to minimize pain, and orchestrating a calm setting all transform the individual's experience before a single dose. I commonly ask trainees to try their discomfort scale once more after proper positioning. The number regularly comes by two. That decline buys time and decreases total drug load.
Guided breathing looks basic, however lots of -responders hurry it. The trick is to pair your breath and matter out loud, sluggish sufficient to feel unpleasant. 5 seconds in, hold for a beat, five seconds out. Utilize your hand on their shoulder to set the tempo. After a minute the jaw unclenches, and you can position the screen leads without a fight.
Cold and heat continue to be low-risk accessories if you value contraindications. Acute strains like cold packs in the initial hours. Spasm-dominant reduced neck and back pain may react to warmth if there is no suspicion of infection or trauma. The training instructs you to ask short, targeted concerns that reveal when a straightforward pack aids more than a second drug.
Documentation Belongs to the Therapy
I treat documents as part of analgesia. Good notes safeguard patients, sustain clinical reasoning, and speed ED decision-making. PUAEME008 drills a basic structure: baseline pain rating, location and high quality descriptors, picked treatment with rationale, the moment of administration, and a re-evaluation at specified periods. If something really feels wrong, compose that down also. "Pain out of proportion to findings" is not a problem, it is an analysis idea. It signals area syndrome, vascular concession, or occult stomach pathology.
Audit groups expect patterns. If every patient reports 10/10 discomfort before and 2/10 after, something is off. Learn to adjust the range with clients. "Zero is absolutely nothing whatsoever, 10 is the worst discomfort you can visualize. Where are you today?" Then anchor it with their own words. After intervention, request for the brand-new number and what changed: "I can relocate my leg currently," or "it still stabs when I breathe." That subtlety helps the following clinician pick up the thread.
Safety Webs and Red Flags
The most seasoned responders carry two psychological manuscripts: one for routine discomfort treatment and one for the exemptions. The device explicitly educates both. Warning consist of sudden extreme headache unlike previous migraines, breast discomfort with diaphoresis and radiation, abdominal discomfort with guarding and hypotension, back pain with neurological deficiencies, and arm or leg discomfort with pallor, pulselessness, or paraesthesia. Analgesia does not stop due to the fact that a red flag exists, yet lines of communication open quickly. You inform getting teams, reduce on-scene time, and keep drug selections conventional if they may mask key signs.
Paediatric pain is its very own world. Kids under-report or misreport, and troubled parents intensify or subdue cues. PUAEME008 uses age-appropriate scales like the Wong-Baker faces or observational devices for preverbal young children. Application comes to be weight-based and margin for mistake narrows. I educate a habit of checking out doses from two independent resources on scene, such as a laminated card and a calculator application, to prevent straightforward transpositions.
Older grownups require a different caution. Kidney feature, polypharmacy, and cognitive standard are frequently unidentified. Low-and-slow dosing, longer monitoring, and early factor to consider of non-opioid accessories lower injury. If a client with an autumn offers with light head strike and a regular examination however takes anticoagulants, analgesia proceeds, however you promote for imaging and cautious handover.
How PUAEME008 Intersects With Other Disciplines
Pain administration programs for nurses and discomfort monitoring programs for physiotherapists often target subacute or persistent problems. Yet there is a productive overlap with this emergency system. Nurses in immediate treatment and remote facilities handle first discussions when ambulance delays stretch. A discomfort monitoring certification training course that includes acute triage abilities, secure breathed in or intranasal alternatives, and surveillance boosts outcomes in those setups. Physiotherapists operating pitch-side or in commercial sites regularly come to be initial clinicians to see injuries. Short programs in pain administration that mirror PUAEME008 concepts assist them secure while waiting for transportation and communicate successfully with receiving teams.
For teams that span roles, an usual language matters. Settle on scale usage, application language, and handover framework. I have seen multidisciplinary teams cut ten mins off scene time simply by lining up on that leads analgesia and that papers. That is not trivia, it is the difference between a comfortable individual and one who shows up clenched and exhausted.
Choosing a Company and What Good Training Looks Like
A supply discomfort administration training course should leave you confident to act under stress, not just to pass an evaluation. Try to find service providers that educate with practical circumstances, actual devices you will utilize in the field, and instructors that have current functional experience. Ask how they deal with damaging events. If the solution is "we cover that in theory," maintain looking. You need to rehearse apnoea drills, vomiting throughout breathing therapy, and taking care of anxiety after ketamine, even if your solution rarely deploys it.
Credentialing issues. Seek a pain management certification lined up with your jurisdiction's requirements and identified by your solution. Paper alone is inadequate, however it opens doors. If your profession arc consists of pain management certificate advanced practice functions, a pain administration accreditation that consists of more comprehensive pharmacology and multidisciplinary case studies matches PUAEME008. Ladder your training attentively: start with the emergency system, include a certificate course in pain monitoring for breadth, after that target professional components pertinent to your setting.

Practical Tips From the Field
These are the small moves that make huge differences over years of practice.
- Prepare your analgesia kit like a cabin, with the very same format every shift. Muscular tissue memory under stress protects against application mistakes and rates delivery. If you share kits throughout teams, standardise the design and tag syringes and atomisers clearly.
Triage your conversations. People suffering find out about one sentence in three. Lead with what issues: "I can decrease your pain now. Here is how it functions." Then deal with permission, risks, and next action in brief, concrete expressions. Check understanding with a question that demands a selection, not a yes/no nod.
Use time checkpoints. In my staffs we call the very first 5-minute reassessment aloud and record it within 60 seconds. That little ritual enhances both safety and security and handover quality.
Treat nausea swiftly. Vomiting undermines client count on and complicates airway security. If your methods allow, match analgesia with an antiemetic for high-risk instances: motion in the back of a rig, traumatic pain, or prior history.
Hand over the person with a pain story. "Showed up to 8/10 discomfort in the best hip, gave breathed in analgesia with a drop to 4/10, then intranasal opioid with a drop to 2/10. Secure vitals throughout. Pain spikes to 6/10 when we roll. Splinted and cushioned." This string guides the getting group to continue the strategy rather than restart from zero.
Assessment and Competency: What to Anticipate on the Day
The functional analysis in PUAEME008 usually unravels across a couple of scenarios and a short created element. For the scenarios, assessors see your flow more than your memory of min details. They wish to see you check for threat, determine and quantify pain, pick a treatment within scope, and after that follow up with tracking and documentation.
If you blank on a dose, claim so, discover the referral, and continue appropriately. That earns more trust fund than thinking. If the client's discomfort does not move, you escalate within the method and call for professional advice if shown. They will likely introduce a curveball: nausea, a drop in saturation after opioid, or a parent that declines an intervention for a child. Remain calm, demonstrate options, and paper deviations.
For the created section, expect short-answer inquiries on consent, contraindications, and side effects. The goal is not to trap you, but to verify that you comprehend why the procedure says what it says.
Connecting PUAEME008 to Job Growth
Many responders see discomfort administration training as a checkbox. That sells it brief. Competence in analgesia associates with total scene management. You interact much better due to the fact that you alleviate enduring early. Individuals speak to you, you collect clearer histories, and your vitals are extra trusted due to the fact that they are not distorted by distress. Supervisors notification. When placements open for group leaders or medical assistance officers, the responders who take care of pain easily typically rise.
For registered nurses, a pain administration qualification training course that includes prehospital components opens up urgent-care functions and occasion medicine job. For physio therapists, adding emergency pain administration skills supports your position on sporting activities medicine teams and work wellness programs. A discomfort management certification does not replace professional degrees, yet it broadens your range safely.
A Note on Principles and Equity
Pain is not distributed uniformly across populaces. Social expression of pain differs, and implied predisposition forms exactly how medical professionals respond. The most effective discomfort administration training courses address this head-on. You discover to apply constant scales, not gut feelings based on who "looks" hurting. You find out to ask open questions, and to verify reported pain also when it exceeds your expectation for the visible injury. In remote and Native neighborhoods, depend on can be slim. Bringing prompt analgesia without rubbing builds bridges. That matters greater than the majority of methods admit.
Final Thoughts: Make Pain Relief a Reputable Habit
PUAEME008 orders routines that experienced clinicians already practice. Evaluate quickly, treat early, combine non-drug and drug actions, screen closely, and record without drama. It provides you a structure that holds when adrenaline spikes or when fatigue dulls judgment at 4 a.m. It likewise produces a common language throughout teams. If you run in emergency situation care and you do not yet hold this unit, it belongs on your checklist of pain monitoring training programs to complete. If you currently hold it, revisit the abilities every year. Bring a coworker, swap roles, and audit emergency pain management each other's charts for a change. The patients will not remember your certificate number. They will certainly bear in mind being heard, being assisted, and having the ability to take a breath without bracing every rib. That is the heart of emergency pain management.
For those building wider paths, mix this training with a discomfort monitoring certification program that explores multimodal methods, pharmacovigilance, and communication across self-controls. Registered nurses that expect to triage and stabilise must consider pain monitoring training for nurses that includes intranasal analgesia, age-specific scales, and rise methods. Medical professionals in sporting activities and musculoskeletal treatment can gain from discomfort management courses for physiotherapists that mirror acute care facts, including splinting and event-side decision-making. Whether you pick a brief training course in pain management or a more comprehensive pain monitoring accreditation course, allow the PUAEME008 mindset anchor your method: relieve pain early, securely, and with sufficient humility to readjust as brand-new information arrives.